What Is Holding Back the Mass Adoption of Spatial Transcriptomics?
Spatial transcriptomics does not have a resolution problem alone. It has an end-to-end system problem spanning discovery to decision-making.
Millions, even tens of millions, of cells appear under the microscope. Gene expression is mapped to spatial coordinates within the tissue, revealing where cancer cells and immune cells interact and where they remain apart. Just a few years ago, this would have been impossible.
But once the screen is closed, more difficult questions remain.
“Which target should we choose?”
“Will this drug reach the interior of the tumor?”
“Which patients should receive it first?”
Today, spatial transcriptomics can generate data at a far greater scale and precision than before, enabled by systems such as ATERA from 10x Genomics. Yet many organizations still do not use it as a routine decision-making tool. The ability to generate data and a company’s reason to repeatedly purchase and use the same type of analysis are two different matters.
The Bottlenecks Are Interconnected
High experimental costs are often cited as the main reason for the slow adoption of spatial transcriptomics. Cost clearly matters. But even if the price of an experiment were cut in half, usage would not necessarily double.
Organizations will not use spatial transcriptomics simply because it is affordable if the objective of the analysis is unclear, suitable tissue is unavailable, experimental results are highly variable, or the resulting data cannot be processed using existing infrastructure. The same is true when the findings cannot be connected to actual drug development decisions or when their reproducibility cannot be trusted.
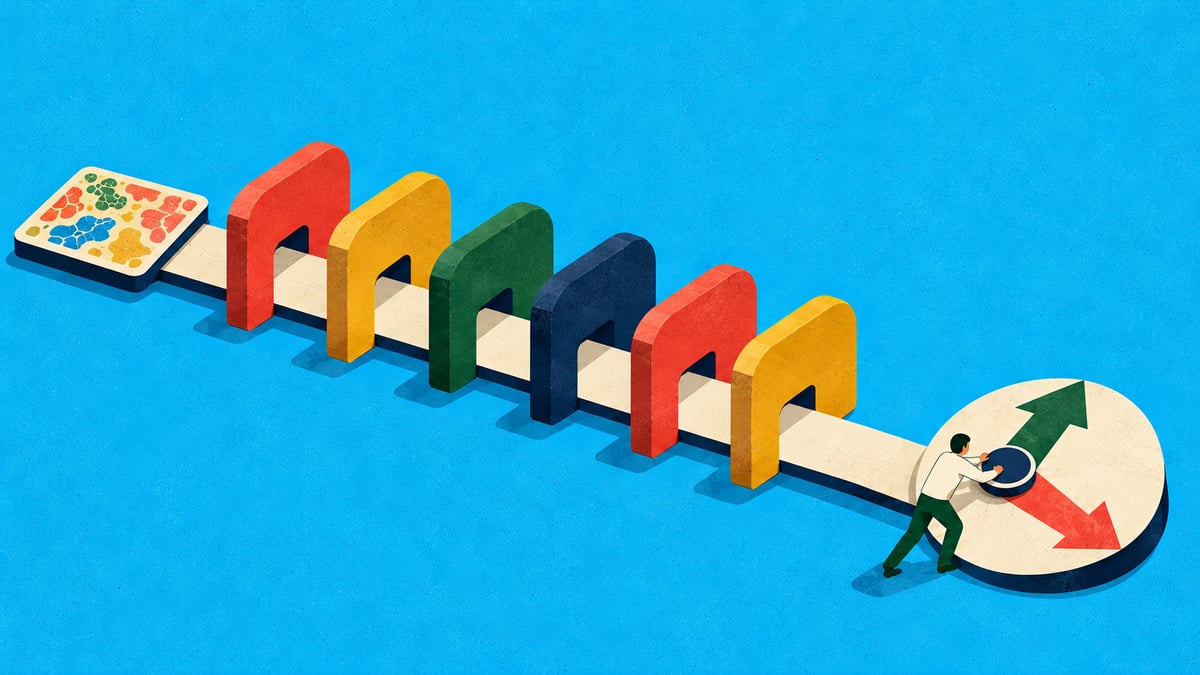
The mass adoption of spatial transcriptomics should therefore be viewed not as a matter of individual technology performance, but as a system-level challenge involving six interconnected stages.
The first is Application. Spatial transcriptomics must go beyond producing a better picture than existing methods. It must meaningfully improve high-cost decisions such as target selection, drug design, and patient stratification.
The second is Tissue. Tissue is not merely experimental material. Cancer type and stage, treatment history, ethnicity, collection site, and whether normal tissue is included for comparison all determine the meaning and generalizability of the data.
The third is Experiment. Scaling is difficult when results depend too heavily on a small number of highly skilled specialists. Automation is not only about speed. It is also about reproducibility, failure rates, and the burden on researchers handling valuable clinical samples and expensive reagents.
The fourth is Data. As the numbers of cells and transcripts increase, so do the requirements for storage, memory, data transfer, preprocessing time, and computing costs. More data does not automatically translate into more knowledge.
The fifth is Analysis. Processing data is not the same as enabling researchers or executives to understand and compare the results and use them to make decisions. Analytical tools must do more than conceal complexity; they must also allow users to examine the analytical process and the evidence behind the results.
The final stage is Trust. It must be demonstrated that results obtained from different tissues, instruments, panels, and analytical methods are comparable to a meaningful degree, and that discoveries at the RNA level can be repeatedly validated at the protein and drug-response levels.
These stages are not independent. A strong application requires an appropriate clinical cohort, while larger numbers of tissue samples require automated experiments. Automation leads to explosive growth in data volume, and large-scale data requires new computing and analytical environments. As analysis becomes more accessible, incorrect results caused by flawed analytical methods can also spread rapidly, increasing the importance of trust and validation.
Ultimately, a problem at any one stage can slow the adoption of the entire industry.
What We Have Learned in Practice
Portrai reached a similar conclusion through real-world drug development projects. At first, the number of genes and cells that could be measured seemed most important. But as discussions with partners became more concrete, the focus shifted from data size, resolution, and volume to the quality of the decisions the data could support.
Which targets better distinguish tumors from normal tissue? How does payload delivery differ depending on antibody properties and tissue architecture, even for the same target? Which patient populations are more likely to benefit from treatment?
Answering these questions requires spatial transcriptomics data, the clinical context of the tissue, experimental quality, computing infrastructure, modeling of drug mechanisms of action, and independent validation to be connected in a single workflow. The ultimate output of spatial transcriptomics should not be a beautiful map, but a better decision.
Of course, not every drug development question requires spatial information. If a question can be answered with a well-validated single biomarker or a low-cost assay, conventional methods may be more appropriate. Mass adoption does not mean replacing every experiment with spatial transcriptomics. It means becoming the most trusted standard tool for problems in which spatial information is critical.
What Will Change Over the Next 3–5 Years?
In an optimistic scenario, declining experimental costs, automation, next-generation computing, and AI-based analysis will advance together, allowing spatial information to become a standard input for drug development.
Realistically, adoption is more likely to begin in areas where the value of spatial context is clear, such as target discovery, prediction of delivery for antibody-drug conjugates and radiopharmaceuticals, and analysis of the tumor microenvironment, rather than expanding across every area at once.
Conversely, if data production continues to increase without demonstrating clinical and economic value, spatial transcriptomics may remain a sophisticated but limited research service. Which future becomes reality will depend on how effectively the six bottlenecks are connected.
Spatial transcriptomics does not have a resolution/plex problem alone. It has an end-to-end adoption problem.
In the next article, we will examine the starting point of this chain: the killer application, or the question, “Exactly which decisions must spatial transcriptomics change for it to be used repeatedly?”